


Medicare reimbursement is changing again in 2027, and the effect will not look the same for every pathology group or laboratory. The final CY 2027 Medicare Physician Fee Schedule (MPFS), effective January 1, 2027, reduces physician conversion factors and changes how practice expenses are allocated. Meanwhile, laboratories paid under the separate Clinical Laboratory Fee Schedule (CLFS) face another set of potential rate adjustments. For leaders planning next year’s budget, the practical question is: which services will be affected, and by how much? The below PDF labeled Table 1 highlights changes in Medicare reimbursement for commonly billed pathology procedures under CY 2027 MPFS, compared to 2026 payment rates.
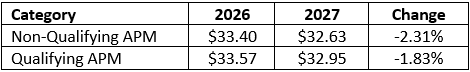
2027 MPFS Conversion Factors
The expiration of the 2.5% temporary payment relief at the end of 2026 is contributing to lower 2027 conversion factor. These translate RVUs into dollars, but they do not tell the full story for an individual practice. A hospital-based pathology group billing mostly professional interpretations may have a different result from a laboratory that bills technical or global services. Comparing code-level payment amounts is the best way to understand the difference.
Surgical Pathology & CPT 88305 Code Family
CPT® 88305 deserves special attention because it represents substantial volume for many surgical pathology practices. Table 1 illustrates a 4.2% reduction in Medicare reimbursement for the global component of CPT 88305 under the CY 2027 MPFS. A seemingly small per-unit payment change can become meaningful when multiplied by thousands of specimens. Other frequently billed services, including 88307, 88309, immunohistochemistry, cytopathology and consultations should be reviewed alongside it. Importantly, professional (-26), technical (-TC) and global payments can move in different directions, so practices should not assume one percentage applies to every component.
Practice Expense and Valuation
CMS is revising the way certain indirect practice expenses are distributed among services. This matters for pathology because the resources behind a professional interpretation differ from those needed to prepare and process a specimen. Practices should review the resulting RVUs rather than assume the change benefits or disadvantages every setting equally. Separately, CMS scrutiny of potentially misvalued services warrants attention, but a valuation review alone does not establish a new daily billing limit or an automatic future cut.
CLFS: A Separate Payment System
Clinical diagnostic laboratory tests are generally reimbursed under the CLFS, not the MPFS. As a result, the physician conversion factor changes discussed above should not be applied to CLFS paid tests. Under the Consolidated Appropriations Act, 2026, private-payer-data-based CLFS reductions can resume in 2027, with reductions limited to 15% per year for affected tests through 2029. That is a ceiling, not a 15% across-the-board cut. Integrated pathology and laboratory organizations should model the MPFS and CLFS portions of revenue separately. The proposed RESULTS Act (Reforming and Enhancing Sustainable Updates to Laboratory Testing Services Act) seeks to improve how private-payer information is used to establish CLFS rates and reduce certain reporting burdens. If enacted, it could provide a more sustainable approach to laboratory reimbursement and greater predictability for budgeting.
Algorithm-only Laboratory Services
Beginning in 2027, CMS is changing how certain stand-alone algorithmic laboratory analyses are classified and reimbursed. Under the finalized Hospital Outpatient Prospective Payment System (OPPS) rule, a limited group of services previously reimbursed under the Clinical Laboratory Fee Schedule (CLFS) will instead be classified as Software as a Medical Service (SaMS) and assigned to New Technology Ambulatory Payment Classifications (APCs). These services involve computational analysis of data generated by an earlier laboratory test, rather than the direct examination of a patient specimen. The change creates important distinctions between traditional laboratory testing and secondary software-based diagnostic analysis. Reimbursement will depend on the specific service, applicable Medicare payment system, and setting of care. For pathology practices, independent laboratories, and health systems, this means reviewing affected CPT/HCPCS codes, confirming payment eligibility and billing requirements, and evaluating potential changes in reimbursement. Importantly, this policy does not move all algorithm-based laboratory tests away from the CLFS; it targets certain stand-alone analyses that CMS considers separate diagnostic services.
Revenue Cycle Priorities
• Compare final 2026 and 2027 rates at the CPT and modifier level, including professional, technical, and global components
• Model revenue impact using actual units, Medicare mix, and locality; review commercial contracts indexed to Medicare
• Load and validate fee schedules, monitor underpayments and denials, and confirm documentation and coding requirements
MIPS and the Transition to MVPs
Medicare quality reporting is changing too. The Merit-based Incentive Payment System (MIPS) continues to link performance to future Medicare payment adjustments, but CMS is moving toward MIPS Value Pathways (MVPs), smaller, more clinically focused sets of quality measures and improvement activities. In the 2027 Final Rule, CMS delayed the mandatory move from traditional MIPS to MVP reporting until the 2031 performance year (affecting 2033 payments). Traditional MIPS remains an option through the 2030 performance year. For pathology groups, particularly hospital-based practices, the extra time is valuable: not every measure reflects the work pathologists perform, and choosing meaningful measures can be difficult. Now is a good time to confirm MIPS eligibility and applicable exemptions, review available MVPs and specialty-relevant measures, and work with a qualified registry or reporting partner to test data capture before the transition becomes mandatory. The goal is not simply to avoid penalties; it is to report quality in a way that better represents the care the practice provides.
Looking Ahead
The CY 2027 Medicare Physician Fee Schedule (MPFS) introduces reimbursement changes that will affect pathology practices and laboratories differently depending on their service mix, billing structure, and payer contracts. Lower conversion factors, changes to practice expense calculations, and reductions to commonly billed procedures, including a 4.2% decrease in the global payment for CPT 88305, create additional financial pressures. Meanwhile, clinical laboratories face separate reimbursement challenges under the Clinical Laboratory Fee Schedule (CLFS), including potential payment reductions beginning in 2027. CMS is also evaluating reimbursement approaches for algorithm-based laboratory services and preparing for the eventual transition from traditional MIPS reporting to MIPS Value Pathways (MVPs).
For pathology and laboratory leaders, the priority is to translate these policy changes into actionable financial and operational strategies. This means modeling reimbursement changes using actual CPT volumes and payer mix, validating updated fee schedules, reviewing Medicare-based commercial contracts, and strengthening coding accuracy, denial management, and underpayment recovery. Practices that proactively identify reimbursement exposure, address operational gaps, and monitor financial performance will be better positioned to protect revenue and navigate the evolving Medicare payment landscape. APS will continue monitoring related legislative developments so laboratory and pathology leaders can translate policy changes into practical financial and operational decisions.
CPT copyright 2025 American Medical Association. All rights reserved.
